
- Electroconvulsive therapy (ECT) uses a brief, controlled electrical current under general anesthesia to treat severe or treatment-resistant conditions.
- It is most often used for major depression that has not responded to other treatments, and sometimes for bipolar disorder, catatonia, or severe mania.
- Modern ECT differs greatly from older portrayals; it is done under anesthesia with muscle relaxants and close monitoring.
- Some studies suggest ECT can work quickly for severe symptoms, though memory effects around the treatment period are a known risk.
- ECT is delivered by psychiatrists and anesthesia teams in a hospital or clinic setting, not at home.
- If you are in crisis or having thoughts of suicide, call or text 988 in the US.
Electroconvulsive therapy (ECT) is a medical treatment in which a carefully controlled electrical current is passed briefly through the brain to produce a short, therapeutic seizure. It is performed under general anesthesia by a specialized team. Despite a reputation shaped by older films and history, modern ECT is a supervised, standardized procedure that many clinicians consider among the more effective options for certain severe mental-health conditions.
This guide explains what ECT is used for, how a modern session works, what the research suggests, the known risks, and how care is arranged. It is general education, not a recommendation for any individual.
What ECT is used for
ECT is most often considered for major depression that has not improved with medications and psychotherapy, or when a faster response is needed—for example, when someone is not eating or drinking, is severely suicidal, or has intense psychotic symptoms. It is also used in some cases of bipolar disorder, severe mania, and catatonia. According to the National Institute of Mental Health and the Mayo Clinic, ECT is generally reserved for severe or treatment-resistant situations rather than used as a first step.
Whether ECT is appropriate depends on the diagnosis, prior treatments, overall health, and personal preferences. It is one option among several, and the decision is made with a psychiatrist after weighing potential benefits against risks.
How modern ECT works
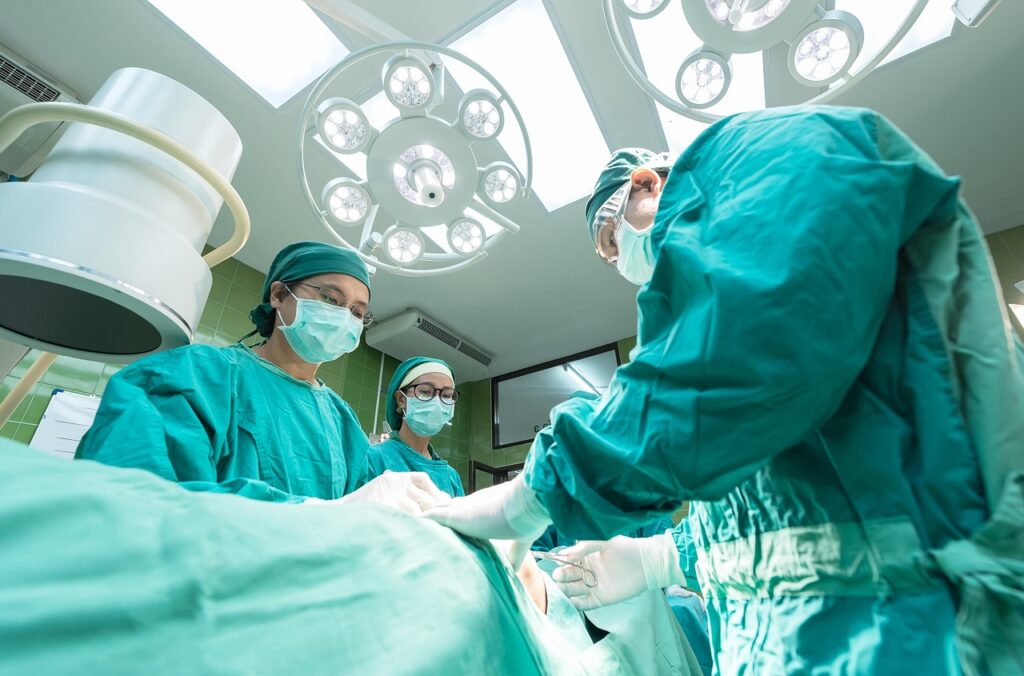
Modern ECT looks very different from its portrayal in old media. Before treatment, you receive general anesthesia so you are asleep, along with a muscle relaxant that prevents the body from convulsing. The care team monitors your heart, brain activity, and breathing throughout. A brief electrical stimulus triggers a controlled seizure lasting typically under a minute, and you wake a short time later in a recovery area.
A full course commonly involves several treatments—often two or three per week over a few weeks—though the exact number varies. Some people later have less frequent “maintenance” sessions to help sustain gains. Electrode placement (for example, on one or both sides of the head) can be adjusted to balance effectiveness against side effects.
| Aspect | What is typical (varies by person) |
|---|---|
| Setting | Hospital or specialized clinic, with an anesthesia team |
| Anesthesia | General anesthesia plus a muscle relaxant |
| Session length | The procedure itself is brief; recovery adds time |
| Course | Often several sessions per week over a few weeks |
| Follow-up | Some people use occasional maintenance sessions |
What the research suggests
Research and clinical experience suggest that ECT can be effective for severe depression, and some studies indicate it may work relatively quickly compared with waiting for medications to take effect. Cochrane and other reviewers have examined ECT across depression and related conditions; overall the evidence supports its use in severe cases while noting that study quality and long-term comparisons vary. The American Psychological Association and NIMH describe ECT as an established option for treatment-resistant illness.
It is important to be measured: ECT is not a cure, responses differ from person to person, and relapse can occur, which is why follow-up care and sometimes maintenance treatment matter. For people considering non-invasive options first, our TMS therapy for depression guide describes a different brain-stimulation approach, and our therapy versus medication overview compares common first-line paths.
Risks and side effects
The most discussed side effect is memory. Some people experience confusion shortly after a session, and gaps in memory for events around the treatment period; for most, these tend to improve over time, though some memory effects can persist. Other possible effects include headache, muscle soreness, and nausea. As with any procedure involving anesthesia, there are anesthesia-related risks, which the team reviews beforehand.
A thorough medical evaluation before ECT helps identify conditions that raise risk. Anyone considering the treatment should discuss their full health history—including heart conditions and prior anesthesia experiences—with the psychiatrist and anesthesiologist.
How care is arranged
ECT is delivered by psychiatrists working with an anesthesia team, typically in a hospital or specialized outpatient setting—not something done at home. Referrals often come from a treating psychiatrist or primary care clinician. You can also ask academic medical centers and larger hospital systems, which frequently offer ECT programs, whether they provide consultations.
Before starting, you should expect informed-consent discussions covering how ECT works, expected benefits, alternatives, and risks, so you can make a decision that fits your goals.
When to seek help
Reach out to a clinician if depression or another mental-health condition is severe, is not responding to current treatment, or is affecting your ability to eat, sleep, work, or stay safe. Severe illness deserves prompt, professional evaluation.
If you are in crisis—having thoughts of suicide or self-harm, or worried about someone who is—call or text 988 (the Suicide and Crisis Lifeline in the US) or go to your nearest emergency department. ECT is a planned treatment, not emergency care.
Frequently asked questions
Is ECT painful? No. It is done under general anesthesia, so you are asleep and do not feel the procedure.
Will I lose my memories? Memory effects around the treatment period are a known risk; for many people they improve over time, though some effects can persist. Discuss this with your psychiatrist.
How many treatments will I need? It varies, but a course often includes several sessions over a few weeks, with possible follow-up sessions later.
Is ECT a last resort? It is generally reserved for severe or treatment-resistant cases, but for some situations—such as when a rapid response is needed—it may be considered earlier.
Can I keep taking my medications? Your psychiatrist and anesthesia team will review all medications beforehand and advise on any adjustments.
Is it done as an inpatient or outpatient? Both are possible depending on your situation and the program.
This article is for general education and is not medical advice. Supplements and therapies affect people differently and can interact with medications or conditions. Talk to your doctor, pharmacist, or a licensed clinician before making changes to your health routine.
Explore more in our wellness guide.
Sources
- National Institute of Mental Health (NIMH) — brain stimulation therapies
- Mayo Clinic — electroconvulsive therapy (ECT) overview
- American Psychological Association (APA) — treatment-resistant depression
- Cochrane — reviews of ECT and depression treatment